Clinical Practice
Genogram intake assessment: a clinician's step-by-step guide
Quick answer
Why collect a genogram at intake?
Most intake forms collect demographics and presenting problems. A genogram intake collects the context that explains why the presenting problem looks the way it does. Three generations of family history, documented in a single diagram, routinely surfaces patterns the client has never articulated: substance use running down the paternal line, a cluster of anxiety disorders on one side, repeated relationship cutoffs that the client is now re-enacting.
The genogram also serves as a therapeutic intervention in itself. Drawing it in session with the client, rather than completing it as a clinician-only artifact, creates a shared map. Clients routinely report insight mid-drawing: “I never noticed that before” is a common response when they see three generations of the same pattern rendered visually.
For social workers doing a kinship or risk assessment, the genogram intake is often the single most information-dense 30 minutes of a case. For nurses completing a family health assessment, it surfaces hereditary risk that a standard medical history form misses.
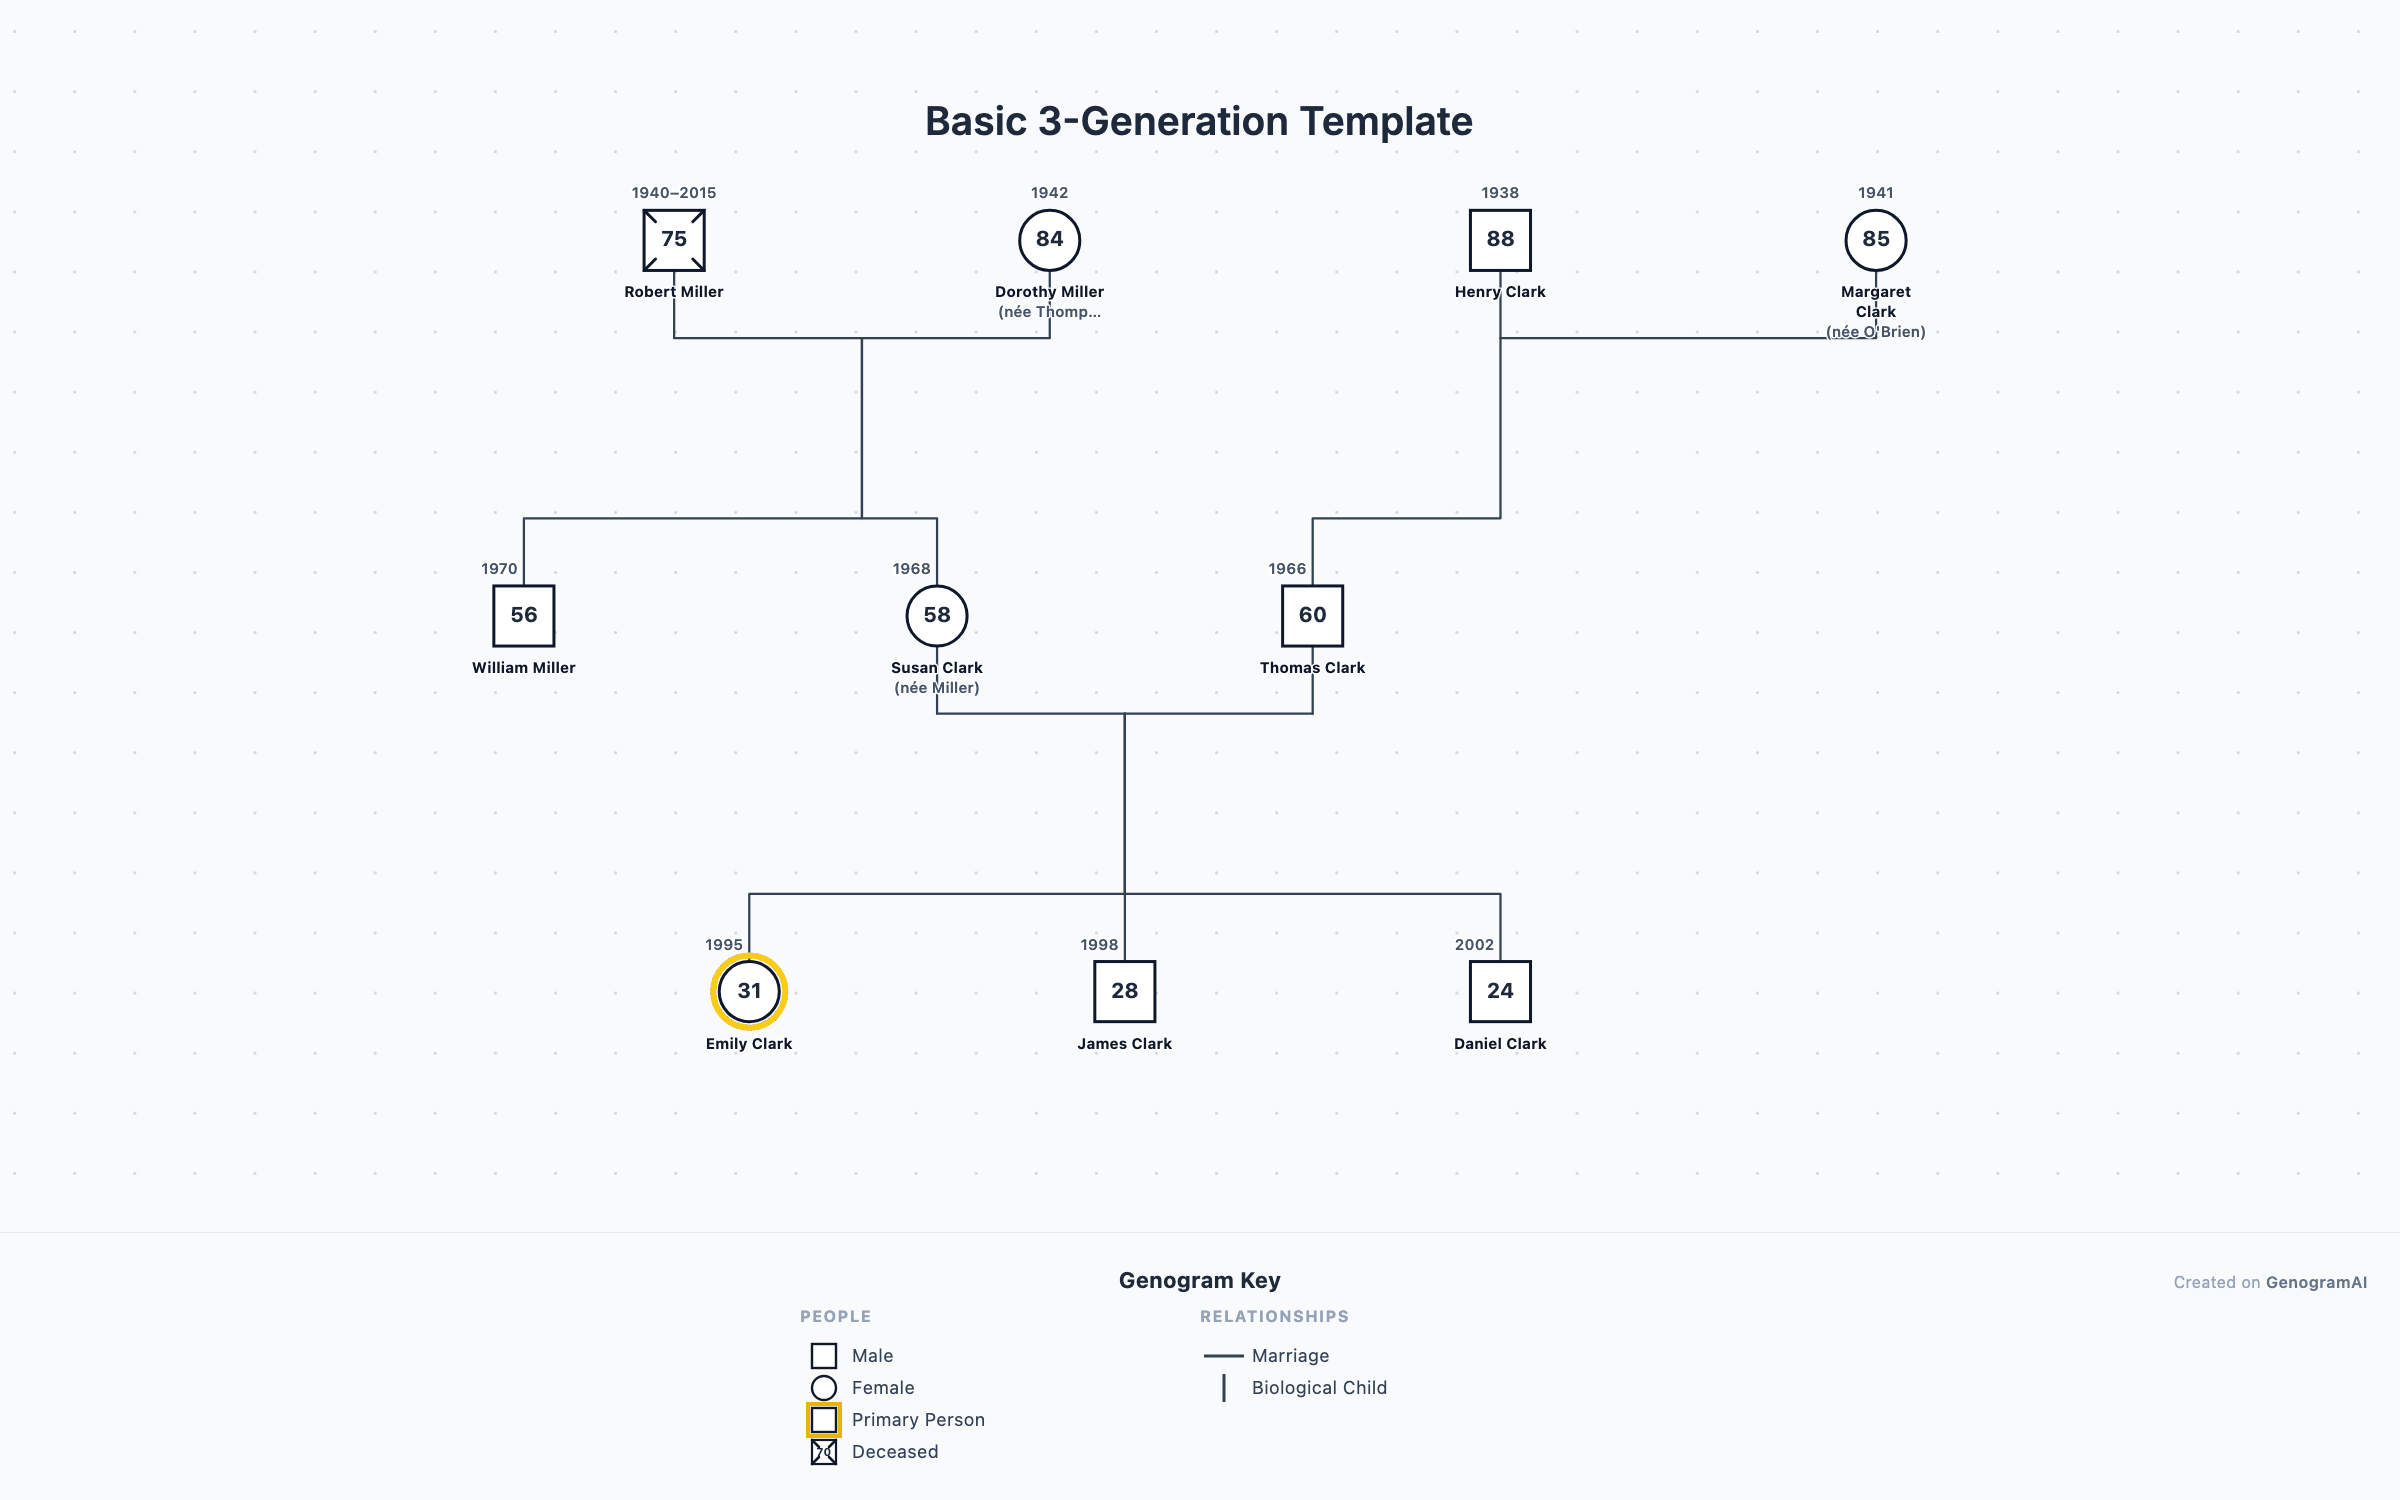
What to gather before you start drawing
- Your purpose. A therapy genogram focuses on emotional patterns and relational dynamics. A medical genogram focuses on hereditary disease. A social work genogram focuses on structure, risk, and resources. Each emphasis shapes which questions you prioritize and which symbols you use most.
- Your notation standard. Standard genogram notation as described by McGoldrick and colleagues is the most widely used in clinical work. Nursing programs often pair the genogram with the Calgary Family Assessment Model (CFAM), which is an assessment framework rather than a notation system, so the symbols themselves usually still follow standard notation. If you’re in a supervisory context, match your supervisor’s conventions. Link the key to the genogram when you document it so any colleague can read it. See the genogram key reference.
- How you’ll document it. Paper works fine for a first session. Digital tools (including GenogramAI) let you build it live, export immediately, and share with the care team without re-drawing. See the AI genogram creator.
The intake question sequence
- 1
Anchor the index person
Draw the client first (double border) with their age. Establish the present moment: current household members, current relationship status. This orients the client and gives you the center of the diagram before you move outward.
Opening question: "Let’s start with you. Who lives in your household right now?" - 2
Map the nuclear family
Move immediately to parents and siblings. Draw the structural lines: birth order of siblings left to right, oldest to youngest. Note ages, and mark deceased members with an X and cause of death if known. This is efficient, factual, and non-threatening; most clients can give you this in five minutes without anxiety.
Questions: "Tell me about your parents — are they living? Together or separated? Do you have brothers or sisters?" - 3
Move to grandparents
Add both sets of grandparents. Note ages and causes of death. Many patterns, particularly medical ones, only become visible at the three-generation level. A client whose father died of a heart attack at 58 may not know that his grandfather died the same way at 54 until you ask. See the three-generation genogram guide.
Questions: "What do you know about your grandparents on each side? Are any of them living? What did they die of?" - 4
Add medical and psychiatric history
Once the structure is drawn, go back through each generation and annotate significant diagnoses: diabetes, cardiovascular disease, cancer, mental health conditions, substance use disorders. Use the client’s language ("he drank a lot") initially, then clarify clinically ("was he ever in treatment for alcohol?").
This layer is critical for medical genograms and for any intake where hereditary risk is relevant. It is also the layer that most frequently surfaces unprocessed family trauma: clients who calmly reported a parent’s early death in step 2 often show affect when you ask, in step 4, what the parent died of and how old the client was at the time.
Questions: "Did anyone in your family have significant health conditions? Any history of depression, anxiety, or other mental health concerns? Alcohol or substance use?" - 5
Add relationship quality
Now add the emotional relationship lines: close, distant, conflictual, cutoff, enmeshed. This is where the genogram shifts from structural inventory to clinical tool. Start with the relationships most relevant to the presenting problem. Most clients need brief psychoeducation here: “I’m going to add some lines that show the quality of the relationship, not just who’s related to whom.”
If the client presents with relationship anxiety, the parent-child emotional lines matter immediately. If the presenting problem is a work conflict, the sibling and peer lines may be more revealing. See the genogram relationship lines reference.
Questions: "How would you describe your relationship with your mother? Close? Complicated? Have you ever had a period where you weren’t speaking?" - 6
Identify patterns and name them
Once the genogram is drawn, pause and look at it with the client. This is the interpretive moment. Name what you see without over-interpreting. For example: "I notice that on your father’s side, we have three generations of men who left the family. I wonder what that’s like for you to look at."
The patterns most worth naming at intake: symptom concentration in one generation, repeated relationship cutoffs, a single family member who carries disproportionate caretaking burden, medical risk clusters that the client hasn’t connected to themselves. See the genogram interpretation guide.
| Step | What you add | Opening question |
|---|---|---|
| 1. Anchor the index person | Client, household, current relationship status | "Let’s start with you. Who lives in your household right now?" |
| 2. Map the nuclear family | Parents, siblings, birth order, deaths | "Tell me about your parents — are they living? Together or separated? Do you have brothers or sisters?" |
| 3. Move to grandparents | Both sets of grandparents, ages, causes of death | "What do you know about your grandparents on each side? Are any of them living? What did they die of?" |
| 4. Add medical and psychiatric history | Diagnoses, mental health, substance use | "Did anyone in your family have significant health conditions? Any history of depression, anxiety, or other mental health concerns? Alcohol or substance use?" |
| 5. Add relationship quality | Close, distant, conflictual, cutoff, enmeshed | "How would you describe your relationship with your mother? Close? Complicated? Have you ever had a period where you weren’t speaking?" |
| 6. Identify patterns and name them | Repeated cutoffs, symptom clusters, caretaking burden | "I notice that on your father’s side, we have three generations of men who left the family. I wonder what that’s like for you to look at." |
How long does a genogram intake take?
| Scope | Steps | Typical time |
|---|---|---|
| Focused structural genogram | 1–3 | 15–20 minutes |
| Full clinical genogram with medical history and relationship quality | 1–5 | 35–50 minutes |
| Interpretive step | 6 | Adds 10–15 minutes |
In a standard 50-minute intake session, you can realistically complete steps 1–4 and begin step 5. Many clinicians spread the genogram over two sessions: structure and history in session one, relationship quality and interpretation in session two. This approach often deepens the material: clients think about it between sessions and arrive with new information.
With an AI-assisted tool, the drawing time drops. Describing the family in plain language while the AI generates the diagram lets you maintain eye contact and conversational flow rather than head-down drawing.
Discipline-specific intake priorities
| Discipline | Prioritize | Pair with |
|---|---|---|
| Social work | Structure, risk, and resources: who is in the household, who is a realistic support, who is a risk factor | Precise dates and relationship status (a CPS genogram can be a legal document) |
| Therapy and counseling | Emotional relationship lines and multigenerational patterns | Later sessions: the genogram is a living document |
| Nursing | Medical and hereditary history: causes of death, ages at diagnosis, first-degree relative conditions | An ecomap of the current support network |
Social work
Prioritize structure, risk, and resources. Who is in the household? What are the relationship qualities around the children? Who is a realistic support? Who is a risk factor? The genogram at a CPS intake is a legal document: be precise about dates, relationship status, and documented patterns. See genograms in social work.
Therapy and counseling
Prioritize emotional relationship lines and multigenerational patterns. The structure matters, but the emotional layer is what makes the genogram therapeutically valuable. Many therapists return to the genogram in later sessions as new material surfaces; it is a living document, not a one-time intake form. See genograms in therapy.
Nursing
Prioritize medical and hereditary history. Causes of death, ages at diagnosis, first-degree relative conditions. For nursing family health assessments, the genogram is frequently paired with an ecomap: the genogram shows the medical history, the ecomap shows the current support network. See the medical genogram guide and ecomap in nursing.
Common intake mistakes
- Drawing before asking. Start the conversation first, sketch the structure as you talk. Drawing in isolation before asking questions produces a structural shell with no clinical depth.
- Stopping at structure. A genogram without relationship lines is a family tree. The clinical value lives in the emotional layer.
- Over-interpreting at intake. Name what you see; hold interpretation lightly. You have one session of data. The client has a lifetime. Stay curious, not conclusive.
- Forgetting to ask about deceased members. Who died, at what age, of what cause, and how the family responded: these are often the most clinically loaded questions in the genogram.
- Not documenting it. A genogram drawn on a napkin and not transferred to the file is clinical work with no continuity. Export it, file it, update it.
How to use the genogram after intake
- A new relationship pattern emerges that resonates with the genogram map
- A client reports a significant family event (death, estrangement, reconciliation)
- You’re stuck and need to reconnect with the systemic context
- Supervision requires a case presentation with family context
- Treatment planning requires family involvement or collateral contacts
In digital tools, updating the genogram takes seconds. In paper files, updating means redrawing. This is one of the practical reasons clinicians increasingly use digital genogram tools for cases where the family system is complex or changing.
Frequently asked questions
How many generations should a genogram intake cover?
Three generations is the clinical standard: grandparents, parents, and the client’s generation. Many patterns only become visible at the three-generation level. A fourth generation is occasionally useful for hereditary medical conditions or when multigenerational trauma is the presenting concern.
Should I draw the genogram in front of the client?
Yes, in most clinical contexts. Drawing together is a collaborative act that makes the client a participant in mapping their own family system rather than a passive subject. It also allows real-time correction: clients will stop you and say "actually, that’s wrong" in ways they might not if reviewing a completed document.
What if the client doesn’t know their family history?
Document what is known and annotate gaps explicitly. "Paternal grandfather: unknown" is valuable clinical information; it often signals a family cutoff or secret that becomes relevant later. Do not skip the question; note the absence.
Is genogram intake appropriate for every client?
Not always in the first session. Clients in acute crisis need stabilization before a historical family mapping conversation. Clients with significant trauma histories may need a therapeutic relationship established before the genogram questions feel safe. Exercise clinical judgment about pacing; the genogram is a tool, not a protocol.
How do I document a genogram in an EHR?
Export the genogram and attach it to the case file. In GenogramAI, PNG export is included on the free plan; PDF, SVG and GEDCOM export come with the Professional and Clinical plans. Some EHR systems (Epic, Cerner) have built-in family history modules; the exported genogram supplements these with the relational and historical layer those modules do not capture.
Build the genogram in session